

Table of Contents
- What Regenerative Medicine for Knees Actually Does
- Comparing Injection Types: PRP, Stem Cell, and Hyaluronic Acid
- Stem Cell Therapy for Knee Osteoarthritis Cost and Financial Planning
- Recovery Time for Knee Regenerative Injections
- FDA Regulations on Regenerative Medicine: What Patients Should Know
- Regenerative Medicine for Knee Rejuvenation vs. Total Knee Replacement
- Conclusion
Last Updated: August 15, 2026
What Regenerative Medicine for Knees Actually Does
Regenerative medicine for knee rejuvenation is a category of biologic therapies that stimulate the body’s own healing mechanisms to repair damaged cartilage, reduce inflammation, and restore joint function, without surgery. Rather than masking pain with medication or replacing the joint entirely, these treatments target the cellular environment where degeneration begins.
The knee depends on healthy cartilage, synovial fluid, meniscus integrity, and surrounding ligament stability to function properly. When any of these components degrades, the entire system compensates, creating the chronic, progressive pain that brings most patients seeking treatment.
How Cartilage Degeneration Leads to Chronic Knee Pain
Cartilage degeneration is the central driver of most knee conditions, including osteoarthritis. Articular cartilage has almost no blood supply, which means it has limited regenerative capacity on its own. Once chondrocytes (the cells that maintain cartilage) begin to break down, joint space narrowing follows, bone-on-bone friction increases, and the synovial fluid loses its protective properties.
This process often spans years before pain becomes debilitating. By the time most patients seek treatment, they’re dealing with a combination of cartilage loss, chronic inflammation, and compensatory muscle imbalances. The goal of regenerative orthopedics is to intervene before that endpoint, shifting the joint environment from ongoing breakdown toward repair and joint homeostasis.
Who Is a Candidate for Regenerative Procedures
Most good candidates for regenerative procedures are patients with mild to moderate osteoarthritis, cartilage degeneration, meniscus-related pain, or ligament tears that haven’t progressed to severe structural collapse. Age is less of a barrier than many expect. Active seniors who want to maintain functional mobility often respond well, particularly when overall health is good and the joint still has preserved space.
Patients who are NOT good candidates include those with advanced bone-on-bone arthritis, severe joint deformity, or active infection. A thorough evaluation, including imaging, is necessary before any recommendation.
Comparing Injection Types: PRP, Stem Cell, and Hyaluronic Acid
Not all regenerative injections work the same way. The three most common options, platelet-rich plasma, mesenchymal stem cell therapy, and hyaluronic acid, have different mechanisms, different evidence profiles, and different ideal use cases.
| Treatment | Source | Primary Mechanism | Best For | Typical Session Count |
|---|---|---|---|---|
| PRP | Patient’s own blood | Growth factors stimulate repair | Mild-moderate OA, soft tissue | 1-3 injections |
| Stem Cell Therapy | Bone marrow or fat tissue | Cellular repair and inflammation modulation | Moderate OA, cartilage loss | 1-2 injections |
| Hyaluronic Acid | Synthetic or rooster-derived | Lubricates joint, cushions cartilage | Mild OA, synovial fluid loss | 3-5 injections |
Platelet-Rich Plasma (PRP) Therapy
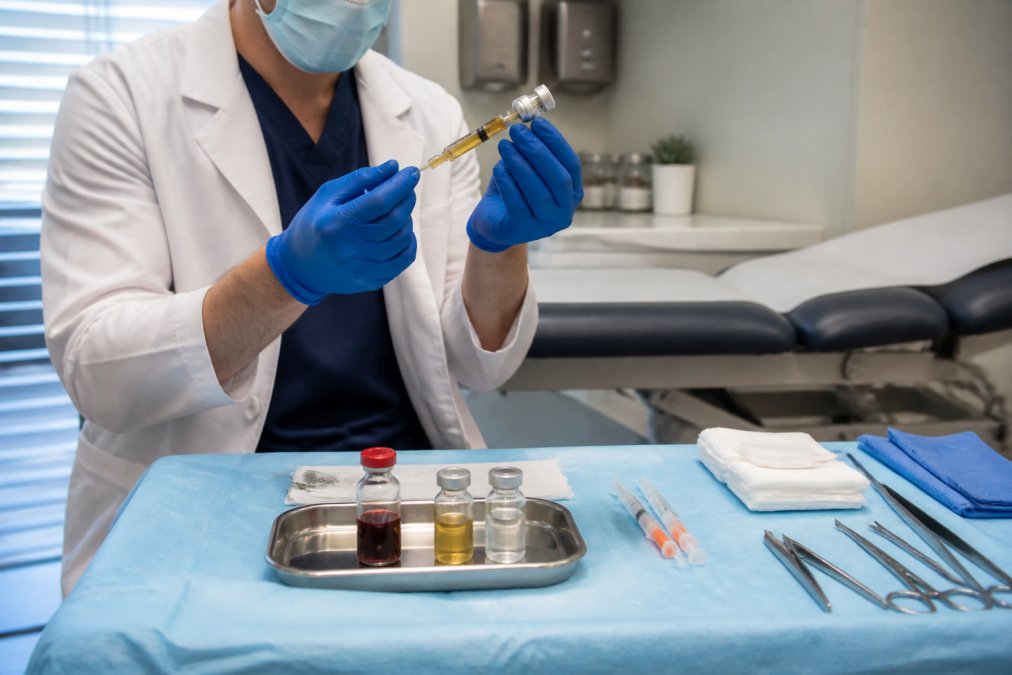
PRP therapy starts with a small blood draw from the patient, which is then centrifuged to concentrate the platelets. That platelet-rich plasma is injected directly into the knee joint. Platelets carry growth factors that signal the body to begin tissue repair, reduce inflammation, and support regenerative capacity.
PRP is the most widely studied of the three options, with growing evidence for its role in pain management and functional improvement in knee osteoarthritis. It works best in joints where some viable tissue remains to respond to those growth factors.
Ask any provider about their PRP preparation protocol before committing. The concentration ratio and leukocyte content significantly affect how the treatment performs in an inflammatory joint environment.
Mesenchymal Stem Cell Therapy
Mesenchymal stem cells are multipotent cells capable of differentiating into cartilage, bone, and connective tissue. Harvested from the patient’s own bone marrow or adipose tissue, they’re processed and injected into the affected joint. The goal is cellular repair: introducing cells with regenerative potential into a joint environment that has lost its ability to self-repair.
Mesenchymal stem cells also modulate the local immune response, reducing the chronic inflammation that accelerates cartilage degeneration. This dual action makes stem cell therapy particularly relevant for patients with moderate cartilage loss where PRP alone may not be sufficient. According to NIH’s National Center for Biotechnology Information on stem cell therapy for osteoarthritis, clinical studies show meaningful improvements in patient-reported outcome measures following mesenchymal stem cell injections.
Hyaluronic Acid Injections
Hyaluronic acid is a naturally occurring component of synovial fluid. As osteoarthritis progresses, the concentration and quality of hyaluronic acid in the joint declines, reducing its lubricating and shock-absorbing properties. Viscosupplementation aims to restore that protective environment.
This is the least "regenerative" of the three options in a strict biological sense. It doesn’t repair tissue or introduce new cells, but it creates a more favorable mechanical environment for the joint, which can meaningfully reduce pain and improve functional mobility in patients with mild to moderate degeneration.
Stem Cell Therapy for Knee Osteoarthritis Cost and Financial Planning
Stem cell therapy for knee osteoarthritis cost varies significantly based on the type of cells used, the harvesting method, the number of joints treated, and the clinic’s preparation protocols.
Most regenerative procedures, including PRP and stem cell injections, are not covered by standard health insurance plans. The FDA’s guidance on human cells, tissues, and cellular products classifies many of these treatments as investigational, which typically excludes them from insurance reimbursement. Health savings accounts (HSAs) or flexible spending accounts (FSAs) can sometimes be applied. Before committing to treatment, patients should confirm with their insurer whether any component of their care qualifies for coverage.
The cost of doing nothing also deserves consideration. Total knee replacement surgery carries substantial financial burden, plus weeks of recovery, anesthesia risk, and the possibility of revision surgery. For patients who are good candidates, regenerative procedures represent a potentially cost-effective alternative.
Be cautious of providers who advertise specific “guaranteed” outcomes or unusually low prices for stem cell procedures. Legitimate regenerative medicine requires proper cell processing, sterile technique, and individualized dosing, all of which have real costs.
Recovery Time for Knee Regenerative Injections
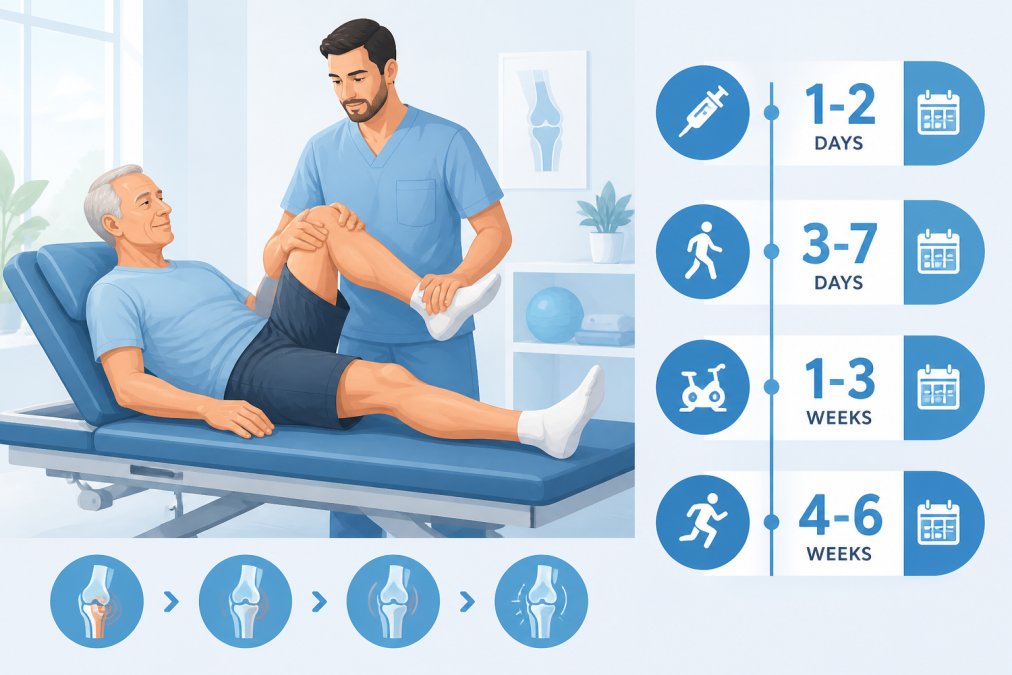
Recovery time for knee regenerative injections is generally shorter than surgical recovery. Most patients experience mild soreness, swelling, or stiffness at the injection site for two to five days following the procedure. Many patients begin noticing reduced pain and improved functional mobility within four to eight weeks, though the full therapeutic effect can take three to six months to develop.
Post-Procedure Rehabilitation Protocols
Post-procedure rehabilitation is where most patients underinvest, and where outcomes diverge most sharply. The injection is the start, not the finish.
Book your consultation today! →
A structured rehabilitation protocol typically includes:
- Days 1-3: Rest the joint, avoid high-impact activity, apply ice as needed for swelling management
- Week 1-2: Begin gentle range-of-motion exercises to prevent stiffness
- Week 3-6: Introduce low-impact strengthening, focus on quadriceps and hip stabilizers
- Week 6-12: Progress to functional movement patterns and activity-specific training
- Month 3+: Full return to recreational activities as tolerated
Strengthening the muscles around the knee reduces compressive load on the joint surface, directly supporting long-term success. Patients who commit to rehabilitation consistently report better outcomes than those who skip this phase.
FDA Regulations on Regenerative Medicine: What Patients Should Know
FDA regulations on regenerative medicine are evolving. The FDA classifies human cell and tissue products under 21 CFR Part 1271, with additional oversight under Section 361 or Section 351 of the Public Health Service Act depending on the degree of manipulation and intended use.
Treatments involving minimal manipulation of autologous cells (your own cells, used for the same general function) occupy a different regulatory category than those involving expanded cell cultures or allogeneic (donor) cells. PRP generally falls under the minimal manipulation framework. Expanded stem cell therapies, particularly those using donor cells, face a higher regulatory bar.
As documented in FDA’s framework for regenerative medicine advanced therapy designation, the agency has been actively working to clarify which products require full biologics license applications versus those that qualify under enforcement discretion policies. Patients should ask any provider directly: is this treatment FDA-cleared, FDA-approved, or operating under enforcement discretion?
Regenerative medicine for knee rejuvenation sits at the intersection of established clinical practice and ongoing regulatory development. Choosing a provider who understands and communicates the current FDA framework is a meaningful indicator of clinical credibility.
Regenerative Medicine for Knee Rejuvenation vs. Total Knee Replacement
Total knee replacement is an effective surgery for end-stage osteoarthritis. When the joint is severely destroyed and structurally compromised, replacement is often the right call. However, total knee replacement is frequently recommended to patients who aren’t yet at that stage.
For patients with moderate cartilage degeneration, persistent pain, and declining mobility, but a joint that still has structural integrity, jumping to orthopedic surgery means accepting significant risks: anesthesia complications, infection, blood clots, a 6-12 month recovery, and the reality that knee implants have a finite lifespan.
Regenerative medicine for knee rejuvenation occupies the space between conservative management and surgical intervention. It’s a non-surgical intervention that aims to delay or avoid total knee replacement by addressing underlying tissue damage while the joint still has regenerative capacity. According to American Academy of Orthopaedic Surgeons clinical practice guidelines, shared decision-making between patient and provider is the standard of care for knee osteoarthritis management.
For patients in the mild-to-moderate range, regenerative procedures offer a meaningful, evidence-supported pathway to pain relief and joint preservation that surgery cannot reverse. Once a knee is replaced, the biological option is gone.
| Factor | Regenerative Medicine | Total Knee Replacement |
|---|---|---|
| Invasiveness | Minimally invasive injection | Major orthopedic surgery |
| Recovery time | Days to weeks | 6-12 months |
| Anesthesia risk | None (local only) | General or spinal |
| Preserves natural joint | Yes | No |
| Best for | Mild to moderate OA | Severe, end-stage OA |
| Reversibility | Fully reversible | Permanent |
| Insurance coverage | Usually not covered | Usually covered |
Advanced Health Center’s approach to knee rejuvenation is built around this philosophy: exhaust every non-surgical option before recommending surgery. With over 40 years of experience managing complex musculoskeletal cases and more than 10,000 patients helped, the clinical team has seen what happens when patients are rushed to the operating table before biologic options are properly explored.
Chronic knee pain doesn’t have to end with a surgical decision. Advanced Health Center offers a multi-faceted, non-surgical approach to knee rejuvenation, addressing the root cause of cartilage degeneration and joint dysfunction through proven regenerative therapies. Our team brings decades of experience to every case, with a focus on restoring functional mobility and long-term pain relief. Book your consultation today and find out whether regenerative medicine is the right path for your knee.
Frequently Asked Questions
Does regenerative medicine actually work for knee osteoarthritis?
Clinical evidence supports regenerative medicine as an effective non-surgical intervention for knee osteoarthritis in appropriately selected patients. PRP and mesenchymal stem cell therapies have shown measurable improvements in patient-reported outcome measures, including reduced pain and improved functional mobility. Results vary based on the severity of cartilage degeneration, the patient's age, and overall health. Patients with mild-to-moderate degenerative joint disease tend to report the strongest therapeutic outcomes. A thorough evaluation is essential before starting any biologic therapy.
How much does stem cell therapy for knee osteoarthritis cost?
Stem cell therapy for knee osteoarthritis is generally not covered by standard health insurance plans, making it an out-of-pocket expense for most patients. Costs vary significantly depending on the type of cells used, the number of injections required, and the clinic's protocols. Because pricing differs widely across providers, the best approach is to schedule a consultation and ask for a detailed treatment plan with itemized costs. Some clinics offer financing options to help manage the expense.
How long does it take to see results from knee regenerative injections?
Most patients begin noticing reduced inflammation and improved joint function within four to eight weeks after their first injection. Full therapeutic outcomes from regenerative medicine for knee rejuvenation, particularly with stem cell therapy, can take three to six months as cellular repair and tissue remodeling progress. PRP injections often produce earlier pain relief. Following your post-procedure rehabilitation protocol consistently is one of the strongest predictors of how quickly you regain functional mobility and long-term joint preservation.
Is regenerative medicine for knees covered by insurance?
Most health insurance plans, including Medicare, currently classify PRP and stem cell knee injections as experimental or investigational, meaning they are typically not covered. Hyaluronic acid injections have broader, though still limited, insurance coverage depending on your plan and diagnosis. Patients should contact their insurer directly to verify benefits and ask about any prior authorization requirements. A clinic's billing team can help clarify what documentation may support a coverage request.
What is the difference between PRP and stem cell therapy for knees?
PRP, or platelet-rich plasma, is created from your own blood. It concentrates growth factors that reduce inflammation and support tissue repair. Stem cell therapy, particularly using mesenchymal stem cells harvested from bone marrow or adipose tissue through autologous cell harvesting, goes a step further by introducing cells with regenerative capacity that can support chondrocyte activity and cartilage restoration. PRP is generally less invasive and lower in cost, while stem cell therapy is better suited to more significant cartilage degeneration or failed prior treatments.
What are the risks and side effects of knee regenerative therapy?
Because most regenerative medicine procedures use autologous material drawn from your own body, the risk of immune rejection is low. Common short-term side effects include localized swelling, soreness, and stiffness at the injection site lasting a few days. Infection is rare but possible with any minimally invasive procedure. The FDA regulates these treatments, and choosing a clinic that operates within compliant protocols significantly reduces risk. Patients on blood thinners or with active infections may not be suitable candidates and should discuss their full medical history during consultation.
This article was written using GrandRanker