

Table of Contents
- What Is Spinal Decompression Therapy and How Does It Work?
- Does Spinal Decompression Therapy Work? What the Clinical Evidence Shows
- Spinal Decompression Therapy Pros and Cons
- Spinal Decompression vs. Physical Therapy: Which Approach Fits Your Back Pain?
- How Many Spinal Decompression Sessions Are Needed for Real Relief?
- Who Is a Good Candidate and Who Should Avoid Spinal Decompression?
- Is Spinal Decompression Therapy Worth It? A Decision Framework
- Frequently Asked Questions
Last Updated: October 12, 2026
What Is Spinal Decompression Therapy and How Does It Work?
Spinal decompression therapy is a non-surgical treatment that gently stretches the spine to relieve pressure on compressed discs and nerves.
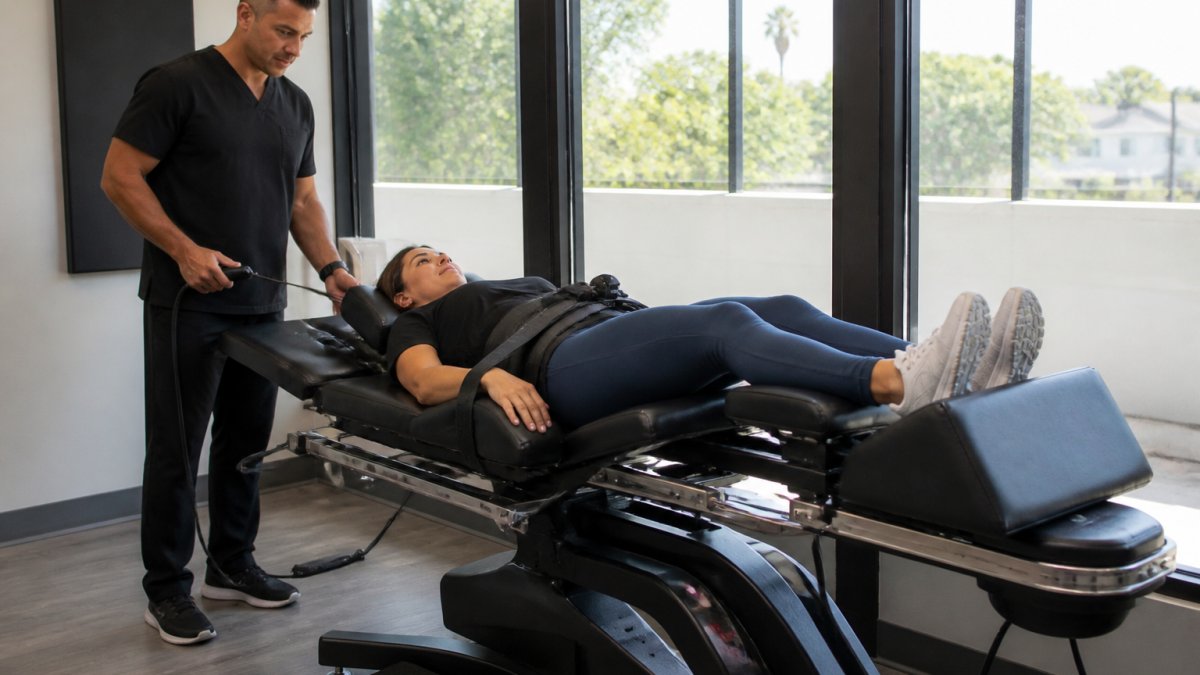
It works through traction: a motorized table slowly pulls the spine apart, creating negative pressure inside the discs that may help bulging or herniated material move back into place while increasing blood flow to support healing.
Here’s what a session typically involves:
- You lie on a specialized table, fully clothed
- A harness secures your hips or shoulders
- The table gently stretches and relaxes in cycles
The pulling force is computer-controlled and adjusts to your body.
Nonsurgical vs. Surgical Decompression: Two Very Different Procedures
These treatments share a name but nothing else. Nonsurgical spinal decompression is a gentle, office-based therapy with no cutting, anesthesia, or hospital stay.
Surgical decompression is a real operation: a surgeon removes bone or disc material pressing on spinal nerves, requiring anesthesia, incisions, and weeks of recovery.
The confusion causes real problems: some patients hear “decompression” and assume surgery, while others think surgery is the only option.
Does Spinal Decompression Therapy Work? What the Clinical Evidence Shows
The honest answer: the evidence is uneven and depends heavily on the condition.
Sciatica from disc compression. Evidence is mixed but leans modestly positive for short-term leg pain and function.
Nonspecific low back pain (no clear disc cause). This is the weakest category.
What the evidence does not show. No strong research demonstrates that nonsurgical decompression durably changes disc anatomy.
A few patterns stand out across the literature and in practice:
- Herniated disc and bulging disc cases have the most supporting evidence
- Sciatica from disc pressure often improves, but so does untreated sciatica
- Chronic lower back pain without a clear disc cause shows the weakest results
The American Academy of Orthopaedic Surgeons overview of low back pain notes that most back pain improves without surgery, which is the correct starting point.
Skipping sessions or stopping early is a common reason treatment underperforms. Discs and irritated nerves respond to consistent, repeated cycles of pressure relief. Partial commitment usually means partial results, and it also makes it impossible to judge whether the treatment would have worked.
How Decompression Compares With Guideline-Supported Conservative Care
Guidelines generally recommend staying active, exercise-based physical therapy, and short-term medication as first-line care for most low back pain. Decompression isn’t typically listed first-line, which doesn’t make it useless, it means the burden of proof is higher and it’s best positioned as an add-on, not a replacement for the basics.
| Approach | Typical evidence position | Cost pattern | Main trade-off |
|---|---|---|---|
| Exercise-based physical therapy | First-line in most guidelines | Often covered; lower per-visit cost | Requires active effort and time |
| Staying active / self-care | First-line | Minimal | Not enough for some disc-related pain |
| Short-term medication | First-line for symptom control | Low to moderate | Treats symptoms, not the cause |
| Nonsurgical decompression | Mixed; strongest for disc-related pain | Higher per-session, often limited coverage | Passive; results may not last without rehab |
| Surgery | Reserved for severe or failing cases | Highest | Real recovery time and surgical risk |
The practical takeaway: decompression is most defensible layered on top of guideline-supported care, not used instead of it. If a clinic offers it as a stand-alone fix and discourages exercise, get a second opinion.
Long-Term Outcomes and Recurrence
Even when decompression helps, relief is often not permanent: meaningful improvement during and shortly after the course, then gradual return of symptoms over months if nothing else changes. That’s true of most passive therapies. Patients who pair decompression with strengthening and movement retraining tend to hold their gains longer. If a clinic can’t tell you the plan after session 20, ask.
Spinal Decompression Therapy Pros and Cons
Every treatment has trade-offs. Here’s the honest breakdown.
Pros:
- Non-surgical and drug-free
- No downtime after sessions
- May help you avoid surgery
Cons:
- Requires multiple sessions over weeks
- Results aren’t guaranteed
- Insurance coverage varies widely
The spinal decompression therapy pros and cons come down to your case: for the right candidate the pros win, and for the wrong one it’s wasted time and money.
| Factor | Spinal Decompression | Physical Therapy | Surgery |
|---|---|---|---|
| Invasiveness | None | None | High |
| Typical duration | 4-6 weeks | 6-12 weeks | One procedure |
| Recovery time | None | None | Weeks to months |
| Best for | Disc issues | Muscle weakness | Severe nerve damage |
| Risk level | Low | Low | Higher |
Spinal Decompression vs. Physical Therapy: Which Approach Fits Your Back Pain?
These two treatments aren’t rivals, they work best together. Where to start depends on your pain source.
Spinal decompression vs physical therapy comes down to what’s causing your pain.
Here’s how we think about it:
- Disc-related pain with leg symptoms → decompression first
- Muscle weakness or instability → physical therapy first
- Mixed causes → combine both
Many patients need both. Decompression relieves pressure while physical therapy rebuilds strength.
Book your consultation today! →
The National Institute of Neurological Disorders and Stroke points out that most people with back pain recover without surgery.
How Many Spinal Decompression Sessions Are Needed for Real Relief?
Most treatment courses run 20 to 30 sessions over 4 to 6 weeks, though some patients need fewer and others more.
The exact number depends on:
- How long you’ve had the problem
- How severe your disc damage is
- How well your body responds
Early sessions relieve pressure and later ones build on that progress. You may notice improvement within a week or two; full results usually take the entire course.
A common mistake is judging the treatment after two or three visits. Discs heal slowly. Give it the full course before deciding if it’s working.
Ask about a mid-course check-in. Around session 10, you should see clear signs of progress. If nothing has changed, it’s worth reassessing rather than pushing through the full course.
Who Is a Good Candidate and Who Should Avoid Spinal Decompression?
Good candidates have disc-related pain that hasn’t responded to rest or basic care, usually mild to moderate, and want to avoid surgery.
You may be a good fit if you have:
- A herniated disc or bulging disc
- Sciatica or leg pain from nerve compression
- Chronic back pain tied to disc pressure
Some people should not do this treatment. That includes anyone with:
- Spinal fractures or tumors
- Severe osteoporosis
- Recent spinal surgery
Screening matters. A proper exam and imaging review should happen before any treatment starts. Skipping that step is a red flag in any clinic.
Is Spinal Decompression Therapy Worth It? A Decision Framework
Is spinal decompression therapy worth it for back pain in your case? “Worth it” is two questions: is it likely to help, and is the cost and time justified versus the alternatives. Answer both before you commit.
Step 1: Match the Treatment to the Cause
Decompression has a plausible mechanism only when a disc is involved. Filter your case:
- Confirmed herniated or bulging disc with leg symptoms → reasonable to consider
- Sciatica from disc compression → reasonable to consider, with the caveat that it often resolves on its own
- Nonspecific low back pain, muscle weakness, or joint arthritis → look elsewhere first
If you don’t have imaging or a clear diagnosis, get one before paying for treatment, starting decompression without knowing the cause is the most common way people waste money on it.
Step 2: Understand the Real Cost and What Insurance Actually Covers
Pricing varies widely, so treat any single number with suspicion. Get the total in writing before you start.
- Per-session cost typically falls in the low-to-mid hundreds of dollars range in most markets, though it can run higher in major metro areas or when bundled with other services.
- Full-course cost is the number that matters. A 20-to-30 session course multiplies that per-session figure quickly, and many clinics bundle decompression with chiropractic adjustments, electrical stimulation, or other add-ons that inflate the total.
- Medicare and Medicaid coverage varies by plan and region, and you should confirm directly rather than assume. The Centers for Medicare & Medicaid Services publishes coverage information, but the rules that apply to you depend on your specific plan.
A clinic that won’t give you a written total, a per-session breakdown, and a clear statement of what your insurance will and won’t cover is a clinic to walk away from. That’s not a red flag about the treatment, it’s a red flag about the business.
Step 3: Set Measurable Goals and a Stop Rule Before You Start
This is the part most people skip, and it protects your wallet. Before session one, write down:
- Your baseline. Rate your pain and function today on a simple 0-to-10 scale, and note how far you can walk or sit before symptoms start.
- Your target. A realistic goal is a meaningful reduction in pain and a clear improvement in one daily activity, not “cured.”
- Your checkpoint. Around session 10, reassess against your baseline. You should see measurable change by then. If nothing has moved, that’s information.
- Your stop rule. If you’re at session 10 with no meaningful improvement, stop and reassess rather than pushing through the full course. Finishing a course that isn’t working doesn’t improve your odds, it just increases the cost.
Put the checkpoint and stop rule in writing and share them with your provider before you start. A clinic confident in its results will welcome the accountability. A clinic that resists it is telling you something.
Step 4: Weigh It Against the Alternatives
Decompression is one option among several, rarely the cheapest or best-supported first step. Exercise-based physical therapy, staying active, and short-term medication are first-line in most guidelines and usually cost less; surgery is reserved for severe or failing cases and carries real recovery time and risk. Decompression sits between them, more targeted than general rehab for disc-related pain, far less invasive than surgery, but with weaker evidence than either.
Safety Screening and Red Flags
Before any treatment, you should be screened for contraindications. Decompression is generally not appropriate with spinal fractures, tumors, severe osteoporosis, recent spinal surgery, pregnancy, or certain metal implants. A proper exam and imaging review should happen first.
Some symptoms mean you should see a physician promptly rather than book a decompression session:
- Loss of bladder or bowel control
- Progressive weakness or numbness in the legs
- Saddle numbness (numbness around the groin or inner thighs)
- Severe pain after trauma, or pain with fever, unexplained weight loss, or a history of cancer
These can signal a serious cause that decompression won’t address and may delay.
The best candidate for spinal decompression has a confirmed disc-related cause, wants to avoid surgery, can commit to the full course, and has a written plan with a checkpoint and a stop rule. If your pain has a different cause, or if you can’t get clear answers on total cost and coverage, spend your time and money elsewhere.
Frequently Asked Questions
Does spinal decompression therapy really work for back pain?
Research shows it can reduce pain and improve function for some people with herniated or bulging discs, especially those with mild to moderate symptoms. Studies report good or excellent results in a portion of patients, but outcomes vary. It tends to work best as part of a broader treatment plan that includes physical therapy and lifestyle changes. If you have severe nerve compression or red-flag symptoms, surgery may be more appropriate.
Who is a good candidate for spinal decompression therapy?
Good candidates typically have chronic lower back pain, sciatica, or a diagnosed herniated or bulging disc without severe nerve damage. People who have not found relief from conservative care like physical therapy or medication often try it. It is not recommended for those with spinal fractures, tumors, severe osteoporosis, or certain implants. A thorough exam and imaging review help determine if you qualify.
How many spinal decompression sessions are usually needed?
Most treatment courses involve 20 to 30 sessions over 4 to 8 weeks, though some people need fewer or more. Sessions typically last 30 to 45 minutes and are scheduled several times per week initially. Your provider may adjust the plan based on how you respond. Improvement often appears within the first few weeks, but lasting changes may take the full course.
Is spinal decompression better than physical therapy for back pain?
They serve different purposes. Physical therapy builds strength and flexibility to support your spine long-term, while spinal decompression targets disc pressure and nerve compression. Many people benefit from combining both. If your pain is driven mainly by a disc issue, decompression may offer quicker symptom relief. For overall spine health and prevention, physical therapy is essential. Your provider can help you decide the right mix.